Does Insulin Resistance Raise Apob?
Understanding Insulin Resistance and ApoB
TL;DR: Yes, insulin resistance can raise ApoB by increasing triglyceride-rich lipoprotein production and reducing particle clearance. Improving insulin sensitivity is often one of the most important steps for lowering ApoB and cardiometabolic risk.
Yes, insulin resistance can raise ApoB. When the body becomes less responsive to insulin, the liver often produces more VLDL particles, which contain ApoB. These particles can later become LDL particles, increasing the total number of atherogenic particles in the bloodstream.
This matters because ApoB reflects the number of lipoprotein particles that can contribute to arterial plaque. LDL cholesterol measures how much cholesterol those particles carry, but ApoB gives a clearer sense of particle burden. This is one reason insulin resistance can create cardiovascular risk even when LDL-C does not look dramatically high.
For the broader prevention framework, see the best ApoB optimization plan. Learn more in our complete guide to longevity.
How Insulin Resistance Affects Lipid Profiles
Insulin resistance affects more than blood glucose. It commonly changes the lipid profile by raising triglycerides, lowering HDL-C, increasing VLDL production, and increasing the number of ApoB-containing particles.
A common pattern is high triglycerides, low HDL-C, and elevated ApoB. LDL-C may be high, normal, or even relatively low, depending on how much cholesterol each particle carries. This is why someone can have low LDL but high ApoB.
In practical terms, insulin resistance can make the lipid profile more atherogenic even before diabetes develops. A fasting glucose or HbA1c may still look acceptable while triglycerides, waist circumference, fasting insulin, or ApoB suggest early metabolic dysfunction.
What Connects Insulin Resistance to ApoB?
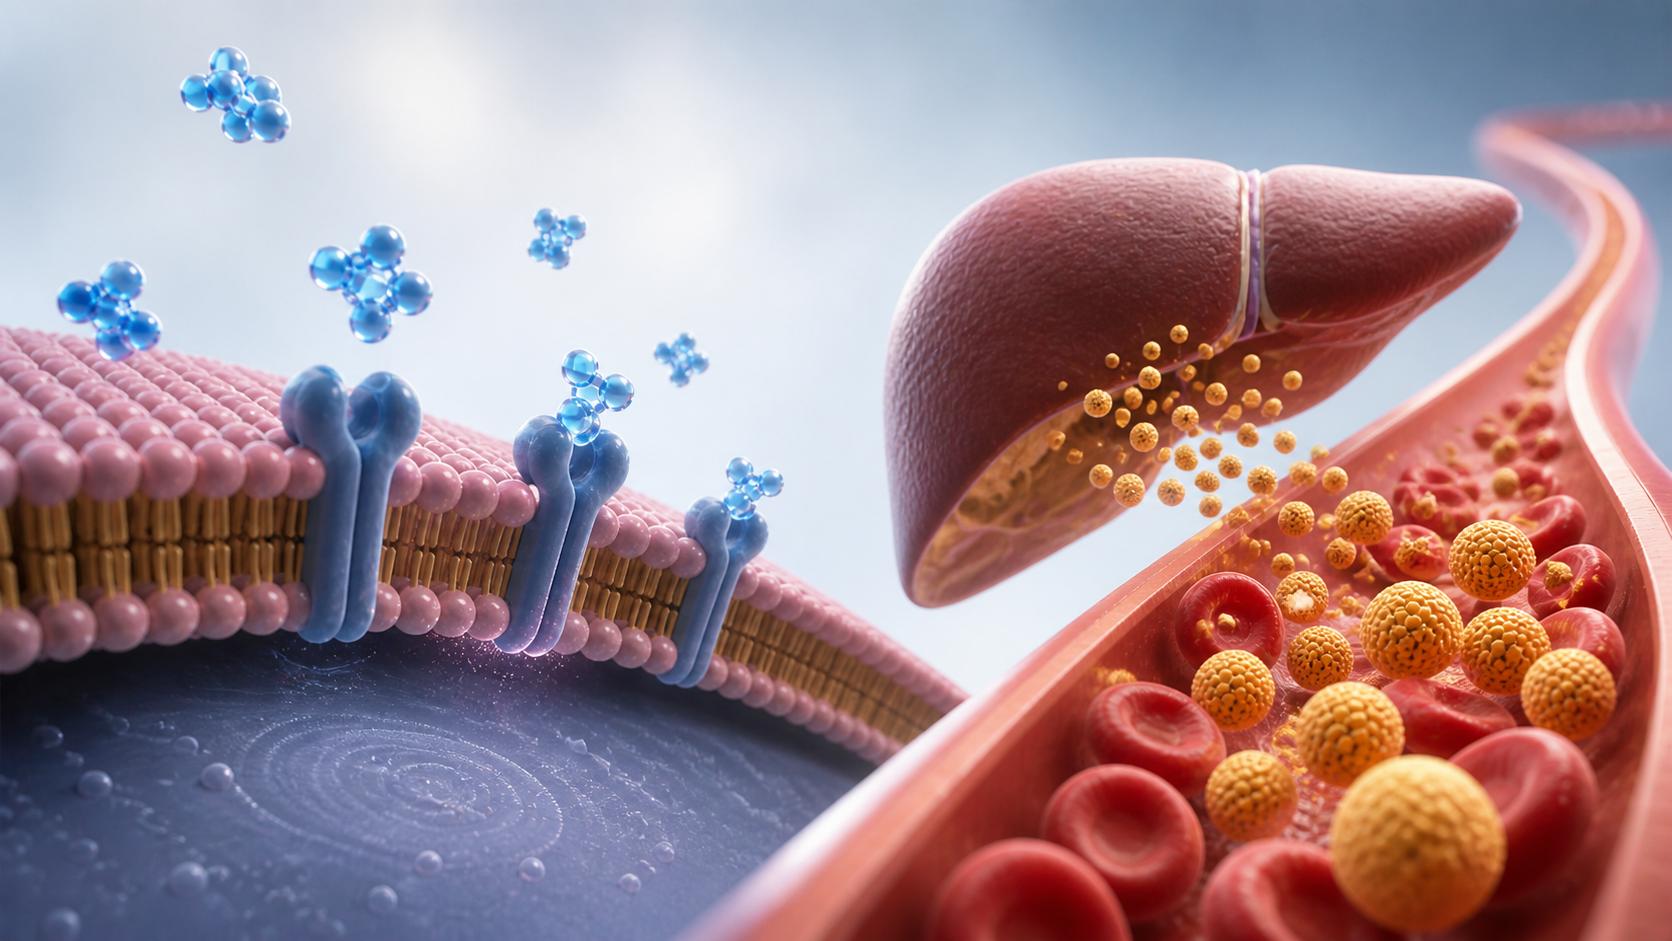
The main link is liver metabolism. When insulin signalling is impaired, fat flow to the liver often increases. The liver then packages more triglycerides into VLDL particles. Because each VLDL particle contains one ApoB molecule, more VLDL production usually means more ApoB particle burden.
Insulin resistance can also reduce clearance of ApoB-containing lipoproteins. This means particles may stay in circulation longer, increasing the chance that they interact with the artery wall and contribute to plaque development.
Does Insulin Resistance Raise ApoB?
Current evidence supports a clear relationship between insulin resistance and higher ApoB. The strongest pattern is seen in people with metabolic syndrome, central obesity, type 2 diabetes, fatty liver, or high triglycerides.
What the Evidence Suggests
Research indicates that insulin resistance increases production of triglyceride-rich lipoproteins and can increase the number of atherogenic particles. ApoB captures this particle number more directly than LDL-C, which is why it can be especially useful in insulin-resistant states.
This does not mean insulin resistance is the only cause of high ApoB. Genetics, saturated fat response, thyroid function, kidney disease, menopause, medications, and body composition can also affect ApoB. However, when ApoB is high alongside high triglycerides, low HDL-C, abdominal fat, or elevated glucose markers, insulin resistance is often an important driver.
Why ApoB Matters More in This Context
Insulin resistance can create cholesterol-poor but particle-rich LDL patterns. In that case, LDL-C may underestimate risk because it measures cholesterol mass, not particle count. ApoB helps reveal whether there are too many atherogenic particles in circulation.
This is also why ApoB should be interpreted alongside triglycerides, non-HDL-C, HDL-C, fasting glucose, HbA1c, blood pressure, waist circumference, and family history. ApoB is highly useful, but it is not a standalone diagnosis.
Why Insulin Resistance Can Increase ApoB
Insulin resistance raises ApoB through several overlapping mechanisms. The most important are increased liver fat availability, higher VLDL secretion, reduced particle clearance, and impaired triglyceride metabolism.
Increased VLDL Production
When insulin resistance develops, fat cells may release more free fatty acids into the bloodstream. The liver takes up these fatty acids and packages them into VLDL particles. More VLDL particles means more ApoB-containing particles.
This is one reason high triglycerides often travel with high ApoB. Omega-3s may help lower triglycerides in some people, but improving insulin sensitivity is usually more foundational when the underlying issue is metabolic dysfunction.
Reduced Clearance of ApoB Particles
Insulin resistance may also reduce the body’s ability to clear ApoB-containing particles efficiently. When particles remain in circulation for longer, ApoB can rise and cardiovascular risk may increase.
Over time, a higher ApoB particle burden increases the likelihood that particles enter the artery wall. This is the mechanism behind the link between ApoB and plaque formation. For more detail, read how ApoB can contribute to plaque.
Managing Insulin Resistance and ApoB Levels
The most effective approach is to reduce the metabolic drivers of ApoB rather than chasing a single marker. In insulin-resistant people, ApoB often improves when triglycerides, waist circumference, liver fat, glucose control, and overall metabolic health improve.
Diet and Lifestyle Strategies
A useful starting point is a whole-food diet built around protein, high-fibre carbohydrates, unsaturated fats, and minimally processed foods. Reducing refined carbohydrates, sugary drinks, frequent snacking, and excess alcohol can help lower triglyceride-rich lipoprotein production.
Soluble fibre from oats, beans, lentils, psyllium, fruit, and vegetables can support LDL-C and ApoB reduction. Weight loss can also lower ApoB when excess visceral fat or fatty liver is contributing to insulin resistance.
Exercise improves insulin sensitivity even before major weight loss occurs. A combination of aerobic exercise, resistance training, and daily movement is typically more effective than relying on one form alone. Sleep quality and stress management also matter because poor sleep and chronic stress can worsen glucose regulation and appetite control.
Medical Interventions and Monitoring
Testing should usually include ApoB, LDL-C, non-HDL-C, triglycerides, HDL-C, fasting glucose, HbA1c, blood pressure, and waist measurement. In some cases, fasting insulin, liver enzymes, Lp(a), thyroid markers, or imaging may also be useful.
Medication may be appropriate when ApoB remains high or overall cardiovascular risk is elevated. Options can include statins, ezetimibe, PCSK9-targeting therapies, or insulin-sensitising medications where clinically appropriate. Supplements such as psyllium, berberine, omega-3s, or red yeast rice may have a role for some people, but they should sit below diet, exercise, weight management, and medical care in the evidence hierarchy.
References and Resources
These resources provide further reading on insulin resistance, ApoB-containing lipoproteins, metabolic syndrome, and cardiovascular risk.
Authoritative Sources on Insulin Resistance and ApoB
-
The Role of Insulin Resistance in Lipoprotein Metabolism
nejm.orgExplains how insulin resistance influences lipoprotein production, triglycerides, and ApoB-containing particles.
-
Insulin Resistance and Atherogenic Lipoproteins
European Heart JournalDiscusses the relationship between insulin resistance, triglyceride-rich lipoproteins, and ApoB-related cardiovascular risk.
-
Metabolic Syndrome, Insulin Resistance, and Lipoproteins
NCBI – PubMed CentralReviews how insulin resistance drives dyslipidemia, including elevated ApoB-containing lipoproteins.
-
American Diabetes Association – Lipid Management
diabetes.orgClinical resources on diabetes, insulin resistance, and lipid risk management.
-
WHO Guidelines on Cardiovascular Risk
who.intProvides broader context on cardiovascular risk factors, including metabolic and lipid-related drivers.
-
American Heart Association – Cholesterol & Lipoproteins
heart.orgPatient-friendly information on cholesterol, lipoproteins, and cardiovascular prevention.
-
Journals on Lipoprotein Metabolism and Insulin Resistance
NCBI – PubMed CentralDetailed research on molecular pathways connecting insulin resistance and ApoB-rich lipoproteins.

-
Medical News Today – Insulin Resistance and Heart Disease
medicalnewstoday.comAccessible overview of how insulin resistance contributes to cardiovascular risk factors.
Frequently Asked Questions
Does insulin resistance directly increase ApoB?
Yes. Insulin resistance can increase liver production of VLDL particles and reduce clearance of ApoB-containing particles. This can raise ApoB and increase cardiometabolic risk.
Can improving insulin sensitivity lower ApoB?
Often, yes. Weight loss where needed, regular exercise, higher fibre intake, improved sleep, and better glucose control can reduce triglyceride-rich particles and may lower ApoB over time.
What lab pattern suggests insulin resistance may be raising ApoB?
Common clues include high triglycerides, low HDL-C, elevated waist circumference, fatty liver, higher fasting glucose or HbA1c, and elevated ApoB. LDL-C may be high, normal, or sometimes deceptively low.
Are medications useful when insulin resistance raises ApoB?
They can be. Lipid-lowering medication may be appropriate if ApoB remains high or cardiovascular risk is elevated. Insulin-sensitising medication may also be considered in specific metabolic contexts under medical supervision.
Conclusion
Insulin resistance can raise ApoB by increasing the production and persistence of ApoB-containing lipoproteins, especially VLDL and LDL particles. This can increase cardiovascular risk even when LDL-C alone does not appear severely elevated.
The most practical response is to treat ApoB and insulin resistance as connected cardiometabolic signals. Improving insulin sensitivity through diet, exercise, weight management, sleep, and targeted medical care can help reduce ApoB particle burden and support long-term cardiovascular prevention.
Find out more information about “Insulin Resistance Raise ApoB”
Search for more resources and information: